
SRU Gallbladder Polyp Calculator (2022 Guidelines)
Click here to see the missing field ⌕

Related Calculators
Risk stratification of acute cholecystitis based on ultrasound and clinical parameters.
Liver lesion classification for hepatocellular carcinoma risk using CT, MRI, ultrasound, and contrast-enhanced ultrasound.
Quantification of liver steatosis using attenuation or signal characteristics on CT and MRI imaging.
Liver volume estimation using imaging measurements with comparison to expected normal values.
More about the SRU Gallbladder Polyp Calculator
The 2022 Society of Radiologists in Ultrasound (SRU) consensus recommendations provide a risk-stratified approach to incidentally detected gallbladder polyps on ultrasound. Most sonographically detected gallbladder polyps smaller than 10 mm are nonneoplastic, commonly cholesterol or inflammatory polyps. The SRU framework was developed to reduce unnecessary surveillance and surgery while identifying lesions that warrant follow-up or surgical consultation on the basis of morphology, size, and interval change.[1]
The 2026 Canadian Association of Radiologists update reviewed the SRU recommendations and the more conservative European guidelines and supported the SRU morphology-based, risk-stratified approach.[3]
When the SRU Algorithm Applies
The SRU pathway is intended for incidentally detected gallbladder polyps evaluated with ultrasound. It should not be applied to patients with primary sclerosing cholangitis (PSC). In patients with PSC, the SRU consensus recommends referral to applicable gastroenterology or other specialty guidance because the malignancy risk and management considerations differ.[1][2]
A lesion with imaging features suspicious for an invasive or malignant gallbladder tumor should not be managed through routine SRU polyp surveillance. Such findings warrant specialist evaluation rather than application of the routine polyp algorithm.[1]
If the ultrasound examination is technically inadequate, the suspected polyp is poorly seen, or the gallbladder is not adequately distended, the SRU consensus supports repeat ultrasound within 1-2 months using optimized grayscale and color or power Doppler technique and appropriate patient preparation.[1]
For a gallbladder lesion larger than 10 mm that cannot be confidently distinguished from tumefactive sludge or adenomyomatosis, the SRU consensus supports short-interval repeat ultrasound within 1-2 months using optimized technique and patient preparation. Contrast-enhanced ultrasound may be used for additional characterization, and MRI may be considered when contrast-enhanced ultrasound is unavailable.[1]
SRU Gallbladder Polyp Risk Categories
The SRU system uses three morphology-based categories.[1]
Extremely Low Risk
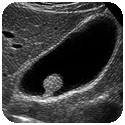
- Pedunculated with a ball-on-the-wall appearance.
- Pedunculated with a thin stalk.
Low Risk
- Pedunculated with a thick or wide stalk.
- Sessile.
If morphology is uncertain between the Extremely Low Risk and Low Risk categories, the SRU consensus supports using the Low Risk category.[1]
Indeterminate Risk
Indeterminate Risk applies when there is focal gallbladder wall thickening of 4 mm or greater adjacent to the polyp that cannot be attributed to wall edema, a mucosal fold, adenomyomatosis, or gallbladder underdistention.[1]
For an otherwise Extremely Low Risk polyp, the SRU recommendations allow optional management as Low Risk when relevant geographic or genetic risk is known, including populations with higher gallbladder cancer incidence.[1][2][3]
Age, coexisting gallstones, polyp vascularity, polyp echogenicity, and the number of polyps are not incorporated into SRU risk stratification.[1][2]
Management by Risk Category and Size
Polyp size should be rounded to the nearest millimeter before applying the SRU thresholds.[1][3]
| SRU category | Polyp size | Recommended management |
|---|---|---|
| Extremely Low Risk | 9 mm or smaller | No follow-up |
| Extremely Low Risk | 10-14 mm | Ultrasound at 6, 12, and 24 months. Surgical consultation is an acceptable alternative |
| Extremely Low Risk | 15 mm or larger | Surgical consultation |
| Low Risk | 6 mm or smaller | No follow-up |
| Low Risk | 7-9 mm | Ultrasound at 12 months |
| Low Risk | 10-14 mm | Ultrasound at 6, 12, 24, and 36 months, or surgical consultation |
| Low Risk | 15 mm or larger | Surgical consultation |
| Indeterminate Risk | 6 mm or smaller | Ultrasound at 6, 12, 24, and 36 months, or surgical consultation |
| Indeterminate Risk | 7 mm or larger | Surgical consultation |
These thresholds are specific to the SRU pathway. Other international gallbladder polyp guidelines use different risk factors and management thresholds.[1][3]
Interval Change During Surveillance
The SRU recommendations recognize that small changes in polyp size can occur as part of the natural history of nonmalignant polyps. Growth of 4 mm or more within 12 months is considered rapid growth.[1]
- An increase of 4 mm or more within 12 months warrants surgical consultation.
- Reaching the surgical-consultation size threshold for the applicable SRU category warrants surgical consultation.
- A decrease of 4 mm or more supports stopping follow-up.
The 2024 SRU clinical-scenarios review further clarifies application of the decrease criterion to shrinking polyps under surveillance.[2][3]
The published SRU follow-up pathway specifies interval-change and surgical-threshold triggers. It does not provide a separate instruction to restart the original baseline surveillance schedule solely because the current follow-up size has entered another surveillance size band. Accordingly, this calculator preserves an already established SRU surveillance plan when none of the defined follow-up triggers is met.[1][2]
Imaging and Reporting Considerations
Morphology should be assessed carefully because it determines the initial SRU category. A thin stalk may be difficult to visualize directly on grayscale ultrasound and may sometimes be inferred from lesion motion or a small vascular stalk. Sessile lesions have a broad-based attachment without a stalk.[1]
Focal wall thickening adjacent to a polyp deserves particular attention. Thickening of 4 mm or greater is considered an Indeterminate Risk feature only after alternative explanations such as edema, mucosal folds, adenomyomatosis, and underdistention have been excluded.[1]
Detectable vascularity alone does not move a polyp into a higher SRU category. Likewise, echogenicity and multiplicity are not used to alter SRU risk stratification.[1][2]
Surgical consultation is not equivalent to an automatic recommendation for cholecystectomy. Surgical decision-making is multifactorial and should account for patient health, operative risk, imaging findings, and shared decision-making.[1]
Important Limitations
The SRU recommendations combine published evidence with expert consensus. The evidence base for gallbladder polyp malignancy risk is limited by selection bias in surgical series, relatively low event rates, and incomplete knowledge of the natural history of small and intermediate-sized polyps.[1][3]
This calculator implements the SRU pathway. It should not be interpreted as a universal gallbladder polyp guideline or as a replacement for radiologist judgment, clinical context, specialist consultation, or local practice standards.
Frequently Asked Questions (FAQs)
Does the SRU gallbladder polyp algorithm apply to patients with primary sclerosing cholangitis?
No. The SRU consensus specifically excludes patients with PSC from its routine risk-stratified pathway and recommends using appropriate specialty guidance because gallbladder lesions in PSC have different malignancy-risk considerations.[1][2]
What should be done when it is unclear whether a polyp has a thin or thick stalk?
When morphology cannot be confidently assigned between Extremely Low Risk and Low Risk, the SRU consensus supports using the Low Risk category.[1]
Do vascularity, echogenicity, or multiple polyps increase the SRU risk category?
No. The SRU consensus does not use vascularity, echogenicity, or polyp multiplicity to increase risk stratification. Management is based on the defined morphology category, size, and relevant interval change.[1][2]
How does a decrease in polyp size affect follow-up?
A decrease of 4 mm or more is an SRU criterion for stopping follow-up. The 2024 clinical-scenarios review further clarified application of this rule to shrinking polyps under surveillance.[2][3]
How does the calculator handle follow-up findings that do not meet an SRU interval-change trigger?
The SRU follow-up pathway identifies rapid growth, reaching the category-specific surgical threshold, and a decrease of 4 mm or more as management-changing triggers. If none is met and the polyp is already under an established SRU surveillance plan, this calculator continues that established plan rather than restarting the baseline schedule from the current size. If a rare follow-up finding simultaneously meets a surgical size threshold and the 4 mm decrease criterion, the published guidance does not explicitly establish which rule takes precedence, so the calculator flags the ambiguity instead of choosing one rule.[1][2]
What if a lesion larger than 10 mm might represent tumefactive sludge or adenomyomatosis?
The SRU consensus supports short-interval repeat ultrasound within 1-2 months with optimized technique and patient preparation. Contrast-enhanced ultrasound may be used for further characterization, and MRI may be considered when contrast-enhanced ultrasound is not readily available.[1]
References
- Kamaya A, Fung C, Szpakowski JL, et al. Management of Incidentally Detected Gallbladder Polyps: Society of Radiologists in Ultrasound Consensus Conference Recommendations. Radiology. 2022;305(2):277-289. doi:10.1148/radiol.213079. PMID: 35787200.
- Knight J, Kamaya A, Fetzer DT, et al. Management of incidentally detected gallbladder polyps: a review of clinical scenarios using the 2022 SRU gallbladder polyp consensus guidelines. Abdom Radiol (NY). 2024;49(9):3158-3165. doi:10.1007/s00261-024-04197-9. PMID: 38411693.
- Fung CI, Kamaya A, Brahm GL, Bird JR, Kirkpatrick IDC. Recommendations for the Management of Incidentally Detected Gallbladder Polyps: Update of the 2020 Canadian Association of Radiologists Recommendations for the Management of Incidental Hepatobiliary Findings in Adults. Can Assoc Radiol J. 2026;77(1):30-32. doi:10.1177/08465371251346728. PMID: 40483673.

Radiologist and Nuclear Medicine Specialist
Neuroradiology fellow at Johns Hopkins University
UT Southwestern Medical Center alumnus